


Author(s) :
Mircea Dediu1, Aurelia Alexandru2, Cristina Ligia Cebotaru3, Petra Curescu4, Polixenia Iorga5, Bogdan Gafton6, Mihai Marinca6, Amedeia Nita7, Mihaela Pașca Feneșan8, Adrian Udrea9, Roxana Lupu10, Gabriela Teodorescu10, Tudor E. Ciuleanu3
1Sanador Oncology Center, Bucharest, Romania;
2Oncology Institute “Prof. Dr. Alexandru Trestioreanu” Bucharest, Romania;
3Oncology Institute “Prof. Dr. Ion Chiricuță” Cluj-Napoca, Romania;
4City Hospital Timișoara, Romania;
5University Emergency Hospital Bucharest, Romania;
6Regional Institute of Oncology Iași, Romania;
7City Hospital Ploiești, Romania;
8Oncohelp Medical Center Timișoara, Romania;
9Medisprof Cancer Center Cluj-Napoca, Romania;
10AstraZeneca Pharma, Bucharest, Romania
Corresponding author: Mircea Dediu, Email: dr.mdediu@gmail.com
Publication History: Received - , Revised - , Accepted - , Published Online - December 2022.
Copyright: © The author(s). Published by Casa Cărții de Știință.
User License: Creative Commons Attribution – NonCommercial (CC BY-NC)

 PDF
 Share
Highlights
• Real-world survival outcomes mirrored randomized trials, with a median rwPFS of 12 months and a median overall survival of 26.4 months in patients treated with first- or second-generation EGFR TKIs in the first-line setting.
• T790M testing at progression was suboptimal (69%), potentially limiting access to effective sequential treatment with osimertinib.
• Treatment attrition after first-line therapy was clinically significant (approximately one in three patients received no further treatment), highlighting the importance of reflex molecular testing and optimal upfront therapeutic selection.
Abstract
Background: REFLECT was a retrospective, non-interventional study conducted in eight countries, including eleven sites from Romania, on patients with advanced stage non-small cell carcinoma (NSCLC).
Aim: To characterize clinical outcomes, treatments and the proportion of T790M EGFR mutation testing in patients with advanced non-small cell lung cancer (NSCLC) receiving first- or second-generation (1G/2G) epidermal growth factor receptor (EGFR) tyrosine kinase inhibitors (TKIs ) as first-line (1L) treatment in the Romanian cohort of an international study.
Methods: Comprehensive data were retrieved from the medical records of ninety patients with EGFR-mutated advanced NSCLC treated with 1G/2G EGFR TKIs between January 2015 and June 2018. All analyses are descriptive.
Results: The median age at lung cancer diagnosis in the Romanian cohort was 67.5 years, with 68% females. The distribution of EGFR TKIs was 50% erlotinib, 31% afatinib, and 19% gefitinib. First line treatment was stopped in 76 (84%) patients due to progression (79%), toxicities (3%), the patient’s decision (1%) or surgery (1%). The median progression- free survival on 1L treatment was 12.0 months (95% CI 10.3-15.6), and the median overall survival from the start of first line therapy was 26.4 months (95% CI 22.4-34.2). EGFR T790M mutation testing was performed on 69% of patients at the time of progression on 1L therapy, with 57% of patients testing positive. Second-line (2L) therapy was started in 63% of patients discontinuing 1L therapy. Third-line treatment was started in 50% of patients discontinuing 2L treatment.
Conclusion: Survival results mirrored those of randomized trials. The suboptimal T790M testing rate (69%) underlines the importance of reflex testing procedures, while attrition rates on 1L (26%) emphasize the need for an upfront selection of the most effective treatments.
Clinicaltrials.gov registration number: NCT04031898 Date of registration on clinicaltrials.gov: 04-Jul-2019
1. Introduction
Lung cancer is a significant health concern; in 2020, in Romania, it ranked first as incidence (12.3% of all new cancer cases) and cancerrelated mortality (19.8% of all cancer deaths) (1). The non-small cell lung carcinoma (NSCLC) is the primary histological type of lung cancer (85%), whereas most patients with NSCLC are usually diagnosed with the disease in advanced / metastatic stage (2,3). During the last decade, the progress in molecular testing led to the identification of actionable oncogenic mutations that transformed the treatment of NSCLC and significantly improved patients’ outcomes compared to chemotherapy (4,5). In about 12% of the Caucasian population with advanced / metastatic NSCLC the epidermal growth factor receptor (EGFR) mutations found on the tyrosine kinase domain (3,4). The EGFR tyrosine kinase inhibitors (TKIs) of first-generation (erlotinib, gefitinib) and second-generation (afatinib, dacomitinib) changed the treatment paradigm (6), and established a new standard front-line treatment of advanced EGFR-mutated (EGFRm) NSCLC (3,7,8). However, after an initial response to these first- or second-generation (1G/2G) EGFR TKIs, the tumor develops resistance that requires a different therapeutic strategy (6,7,9). In 50-60% of cases, the resistance to treatment with 1G/2G TKIs is mediated by the T790M mutation in the EGFRdomain (3,10). The thirdgeneration EGFR TKI osimertinib targets both EGFR sensitizing, and EGFR T790M acquired mutations and demonstrated significant overall survival benefit as first-line (1L) treatment compared to erlotinib or gefitinib (11), and is currently the preferred option of advanced EGFRm NSCLC (12).
In oncology, real-world studies play an essential role in informing clinicians and policymakers about the clinical characteristics of patients treated in routine clinical practice and the effectiveness and safety profile of approved medicines, complementing thus the data derived from randomized trials (13,14). Several realworld evidence focused on 1G/2G TKIs use in EGFRm NSCLC across various geographies (15). A recent medical chart review entitled REFLECT (“Real-world treatment patterns, clinical outcomes, and EGFR / T790M testing practices in EGFR-mutated advanced non– smalL cEll lung Cancer patients receiving First-Line EGFR TKI Therapy”; clinicaltrials.gov ID: NCT04031898) described clinical outcomes, treatment patterns, EGFR / T790M testing practices and attrition rates in 896 patients receiving 1L 1G/2G EGFR TKIs in seven smalland medium-sized European countries, and Israel (16). This study showed that one-third of patients (33%) did not receive any other treatment after discontinuing 1L EGFR TKI. Only twothirds (71%) of the patients progressing on 1L EGFR TKIs were tested for the presence of T790Mresistance mutation.
The analysis of Romanian patients’ data included in the REFLECT study aims to provide a better understanding of real-life clinical outcomes, type of treatments, and proportion of T790M testing in patients receiving 1L 1G/2G EGFR TKI therapy for their advanced EGFRm NSCLC in this country.
2. Methods
2.1. Study design
REFLECT was a retrospective, noninterventional chart review study conducted from May to December 2019 in 49 study sites from Europe and Israel (16), which included 11 (22%) sites from Romania. The results of the Romanian cohort are presented here.
The study was performed in accordance with the ethical principles of the Declaration of Helsinki, Good Clinical Practice, and local regulations for observational studies The Ethics Committees approved the study protocol and study conducted in all participating countries. In Romania, the National Bioethics Committee for Medicines and Medical Devices approved the protocol (3SNI/13.05.2019) with a waiver of informed consent.
2.2. Patients
Eligible patients were adults with confirmed locally advanced or metastatic EGFRm NSCLC, initiated on a 1G/2G EGFR TKI (afatinib, erlotinib or gefitinib) as 1L treatment between January 01, 2015 and June 30, 2018. At the time of data collection, patients could have been alive or deceased. Exclusion criteria included enrolment in an interventional clinical trial for an experimental treatment for EGFRm NSCLC, administration of any other systemic therapy for advanced disease before 1L EGFR TKI and missing/unknown critical study information such as dates of initial NSCLC diagnosis, progression to advanced disease, the start of 1L TKI therapy, death or last available follow-up.
Eligible patients were enrolled consecutively, in the chronological order of initiating the 1L treatment with a 1G/2G EGFR TKI.
2.3. Objectives and outcomes measures
The primary objectives were the proportion of patients with advanced EGFRm NSCLC progressing on 1L 1G/2G EGFR TKI, real-world progression free survival (rwPFS) time and, the proportion of patients receiving second-line (2L) treatment, and types of 2L therapies. Secondary objectives and measures included baseline patient characteristics, rates of T790M mutation testing in patients progressing on 1L therapy, treatment patterns, and attrition rates in subsequent lines, the proportion of patients receiving osimertinib (including the line), proportion and characteristics of patients with central nervous system (CNS) metastases and leptomeningeal disease (LMD) and overall survival (OS).
The real-world time to disease progression was measured from the start of 1L treatment until the first documented, progression that was defined as radiological progression, the beginning of a new therapy, clinical progression evaluated by the treating physician, or death. Treatment patterns were assessed from the 1L 1G/2G EGFR TKI start until the last available followup, or death.
2.4. Statistical methods
Considering this study’s the exploratory and descriptive nature, no formal hypothesis was defined in REFLECT. All analyses are descriptive. Results were summarized using means, medians, standard deviations (SD), and ranges for continuous variables and frequencies for categorical variables. The median rwPFS and OS with 95% confidence intervals (CI) were calculated with Kaplan-Meier methods.
3. Results
3.1. Study sites characteristics
The Romanian study sites included 6 (55%) regional or national cancer centers, 2 (18%) teaching university hospitals, 2 (18%) private hospitals, and 1 (9%) non-teaching hospital. Only three (27%) study sites provided in-house genetic testing services, with EGFR mutation tested reflex in almost half of participating centers (Table 1).
3.2. Patient characteristics
In total, Romanian investigators collected data from the medical records of 90 eligible patients. The median age at the time of diagnosis of the advanced NSCLC was 67.5 (range 34-86) years with 68% of patients being females. In all but two cases, the histological type was adenocarcinoma, and most patients (87%) had initial metastatic stage at diagnosis (Table 2). The median follow-up time was 19.8 (range 3.1-46.9) months.
The EGFR mutation status was determined from tissue biopsy (94%), liquid biopsy (4%) or cytology specimen (1%).
Table 1. Genetic testing characteristics in participating study sites
| Characteristic | N=11 n (%) |
|---|---|
| In-house genetic testing | |
| Yes | 3 (27) |
| No, with patients being referred to: | 8 (73) |
| Central (regional/national) genetic laboratory | 1 (9) |
| Affiliated genetic laboratory | 1 (9) |
| Private genetic laboratory | 6 (55) |
| Reflex EGFR mutation testing (at the time of advanced / metastatic stage diagnosis) | 5 (46) |
| Reflex T790M mutation testing | 4 (36) |
Abbreviations: 1L=first-line; EGFR=Epidermal Growth Factor Receptor; TKI=tyrosine kinase inhibitor
Table 2. Clinical characteristics at the time of initial NSCLC diagnosis
| Characteristic | All patients N=90 |
|---|---|
| Age, median (range), years | 67.5 (34-86) |
| Sex: female / male, n (%) | 61 (68) / 29 (32) |
| Smoking status | |
| – Current smoker | 4 (4) |
| – Former smoker | 18 (20) |
| – Never smoker | 49 (54) |
| – Unknown | 19 (21) |
| Histology | |
| – Adenocarcinoma | 88 (98) |
| – Mixed histology | 1 (1) |
| – Squamous cell carcinoma | 1 (1) |
| Stage | |
| – Early stage (IA, IB, IIA, IIB) | 6 (7) |
| – Limited regional (IIIA) | 2 (2) |
| – Locally advanced (IIIB) | 3 (3) |
| – Metastatic (IV) | 78 (87) |
| – Unknown | 1 (1) |
| ECOG performance status | |
| – 0 | 13 (14) |
| – 1 | 51 (57) |
| – 2 | 15 (17) |
| – 3 | 2 (2) |
| – Unknown | 9 (10) |
| Site of distant metastases* | |
| – Adrenal | 10 (11) |
| – Bone | 26 (29) |
| – Brain | 17 (19) |
| – Liver | 17 (19) |
| – Lung | 51 (57) |
| – Lymph nodes | 20 (22) |
| – Pleura | 33 (37) |
| – Other** | 4 (4) |
| EGFR mutations | |
| – Exon 19 deletion | 44 (49) |
| – L858R | 31 (34) |
| – Uncommon EGFR mutations | 15 (17) |
*Pooled data. Some patients presented multiple metastatic sites at the time of initial diagnosis of NSCLC.
**Other sites of distant metastases included: spleen (2 patients), pericardium (1 patient) and peritoneum (1 patient). Abbreviations: ECOG=Eastern Cooperative Oncology Group, EGFR=Epidermal Growth Factor Receptor, NSCLC=nonsmall cell lung cancer
3.3. 1L EGFR TKI therapy characteristics
The distribution of 1L 1G/2G EGFR TKI therapies was erlotinib 50%, afatinib 31% and gefitinib 19%. Most 1L treatments were administered in monotherapy (92%). At the time of data extraction, 76 (84%) patients discontinued the 1L EGFR TKI therapy due to per-protocol progression events (n=71 (79%)), toxicities (n=3 (3%)), patient’s decision (n=1 (1%)) and surgery (n=1 (1%)) (Figure. 1). All five (6%) patients discontinuing 1L EGFR TKI without documented progression did not start any other treatment line. First-line treatment was continued by 14 (16%) patients.
Relative to the entire cohort, the 1L progression events included radiological progression in 51 (57%) patients, clinical progression in 11 (12%) patients, death in eight (9%) cases and start of a new line of treatment without documented progression for one (1%) patient.
Median rwPFS was 12.0 (95% CI 10.3- 15.6) months (Figure. 2A), with estimated 12-, 24-, and 36-month event-free probabilities of 50%, 21%, and 7%, respectively. Median OS was 26.4 (95% CI 22.4-34.2) months (Figure. 2B), with estimated 12-, 24, and 36-month probabilities of survival of 80%, 58%, and 35%, respectively.
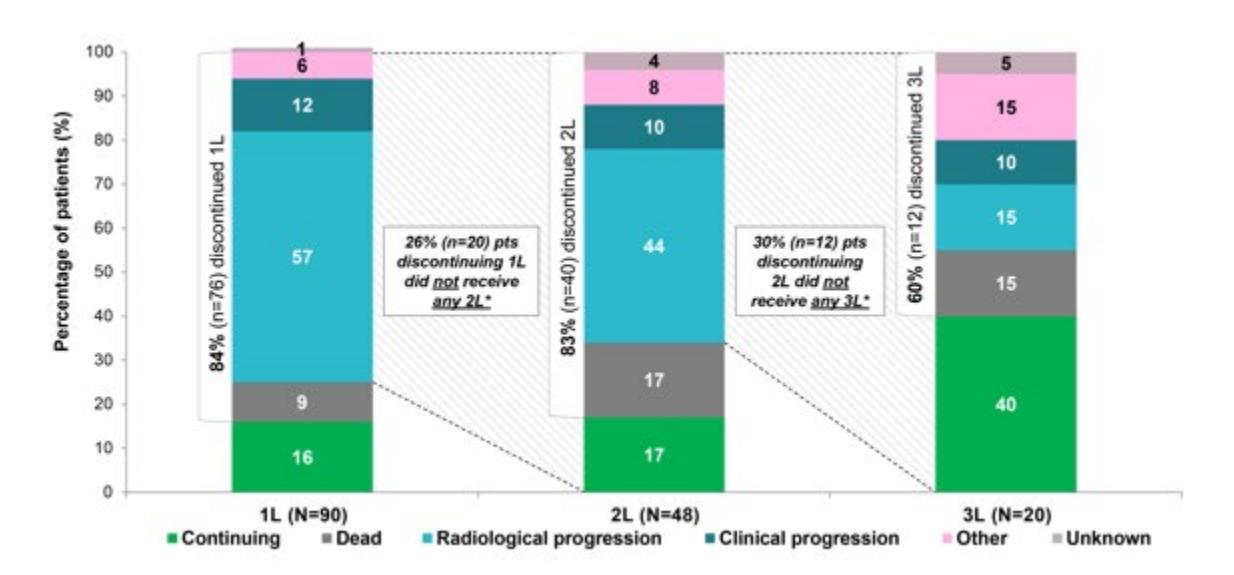
Figure 1. Reasons to discontinue 1L EGFR TKI, 2L and 3L in the Romanian cohort
*The count excludes deceased patients in each line. Due to rounding, percentages may not always be 100%. Note: The patient discontinuing 1L from unknown reasons started a new therapy line without documented progression, which is considered a per-protocol event.
3.4. Second line treatment patterns and attrition rates
Of the 76 patients who discontinued 1L EGFR TKI therapy (Figure 1), 48 (63%) started second-line (2L) treatment and 28 (37%) did not receive any further treatment. Excluding patients deceased on 1L treatment (n=8, 11%), a total of 20 (26%) patients discontinuing 1L did not receive any subsequent treatment. The 2L treatment included osimertinib (52%), chemotherapy (46%), and targeted therapy afatinib (2%). At the time of data collection, 8 (17%) patients continued 2L.
3.5. T790M testing and osimertinib treatment
Of the 71 patients progressing on 1L EGFR TKI, the T790M mutation testing was reported for 49 (69%) patients, yielding positive results in 28 (57%) cases (31% from the enrolled population). The T790M testing was performed via liquid biopsy (67%), tissue biopsy (25%) or cytology (6%) (unknown 2%), after a mean (SD) time of 13.8 (8.5) months since the start of 1L TKI therapy.

Note: Survival probability at 36 months (95% CI) was 7% (2-16%).
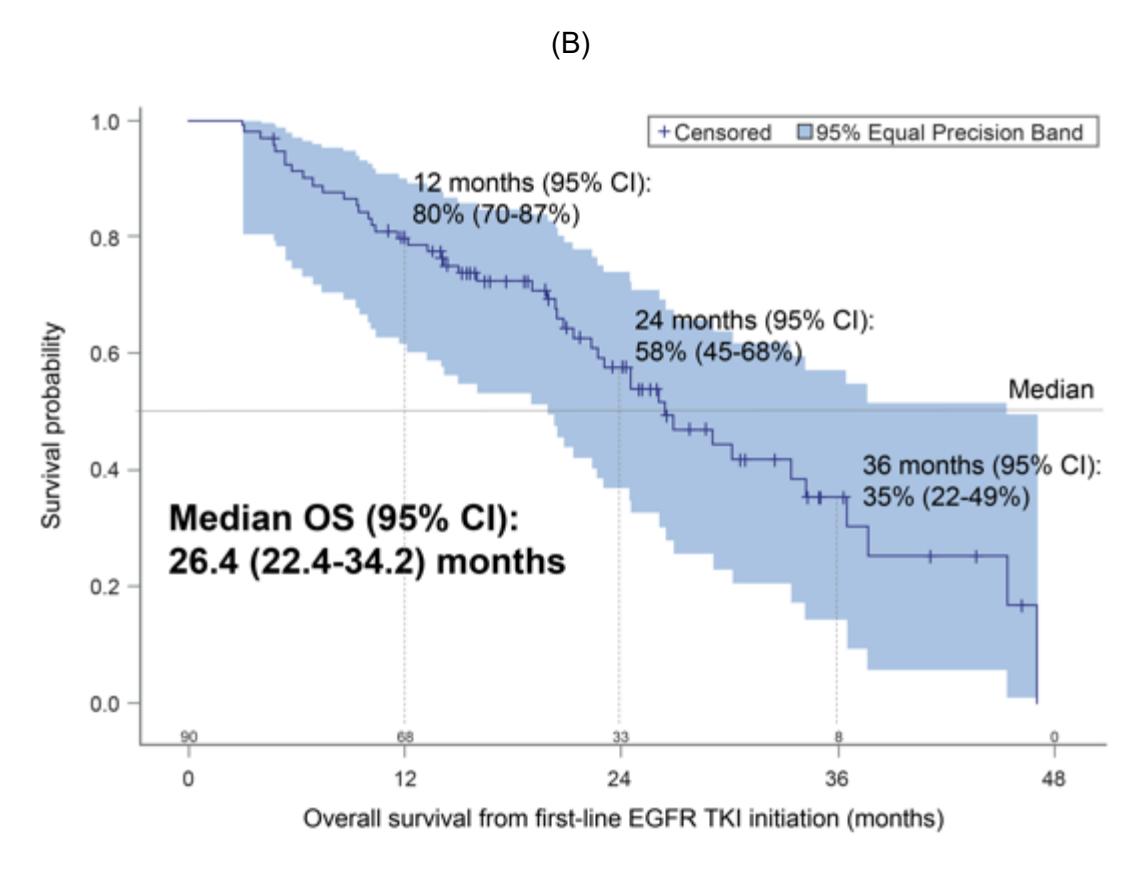
Figure 2. Survival outcomes on 1L 1G/2G EGFR TKI therapy: (A) real-world progression free survival (rwPFS) and (B) overall survival (OS)
Of the 49 patients progressing on 1L EGFR TKI and tested for T790M mutation, 43 (88%) received 2L treatment with osimertinib (n=25 (58%)) or chemotherapy (n=18, 42%). All but one patient tested positive for T790M mutation received osimertinib post-progression (n=27 (96%)): most (n=25, 89%) as 2L treatment, 1 (4%) as 3L and 1 (4%) as 4L treatment. Of the 22 patients progressing on 1L EGFR TKI and not tested for T790M mutation, only 5 (23%) received 2L treatment with chemotherapy (n=4 (80%)) or targeted therapy (afatinib, n=1, 20%).
3.6. Third and subsequent lines treatment patterns
Of the 40 patients discontinuing 2L treatment (Figure. 1), half (n=20, 50%) started 3L. Excluding patients deceased on 2L treatment (n=8, 20%), a total of 12 (30%) patients discontinuing 2L did not receive subsequent treatments. The 3L treatments included chemotherapy (75%), immune therapy nivolumab (20%) and osimertinib (5%). At the time of data collection, 8 (40%) patients continued 3L.
Only 3 patients received 4L treatment: 2 chemotherapy and 1 osimertinib. Two patients died on 4L, and 1 patient started 5L with erlotinib, with radiological progression reported on 5L and no further treatment line.
3.7. CNS metastases and LMD
In total, CNS metastases were reported for 30 (33%) patients: for 19 (21%) patients the metastases were present at the start of the 1L EGFR TKI therapy. Eleven (12%) cases occurred during treatment after a median of 9.2 (range 3.6-23.7) months. The median age of all patients with CNS metastases was 67.5 (42-86) years, and 63% were females. The diagnosis of CNS metastases was made using computed tomography or magnetic resonance imaging scans in most cases (97%) and tissue biopsy in 1 case. Treatments recorded in 88% of patients with CNS metastases included whole brain radiation therapy (63%), stereotactic radiosurgery (13%), targeted therapy (13%), chemotherapy (7%) and surgical resection (3%); in 10% of cases no treatment and for 2% other (unspecified) were recorded. The median OS from the first brain lesion diagnosis was 25.6 (95% CI: 15.3- 32.7) months in patients with CNS metastases at the start of 1L EGFR TKI treatment, and 5.4 (95% CI: 0.6-18.8) months in patients with CNS metastases developed during treatment.
LMD was reported for one patient after the start of the 1L EGFR TKI treatment. The LMD diagnosis was based on imaging scans, after a median of 20.1 months from the start of 1L EGFR TKI.
4. Discussion
To our knowledge, this is the first detailed analysis performed in Romania related to clinical outcomes, type of treatments, and T790M testing rates in patients with advanced EGFR mNSCLC receiving a 1G/2G EGFR TKI as 1L treatment during 2015-2018. The median rwPFS in our cohort was 12.0 (95% CI 10.3- 15.6) months and median OS 26.4 (95% CI 22.4-34.2) months, similar to the rwPFS of 13.0 (95% CI 12.3-14.1) months and median OS of 26.2 (95% CI 23.6-28.4) months reported at the entire study level (16). Our findings are comparable to those reported in the registration trials of the 1G/2G EGFR TKIs (17,18). We found these results encouraging for a country from Central and South-Eastern Europe, regions with high mortality-to-incidence ratio (19) and still suboptimal access to innovative treatments (20).
In our cohort the 1L EGFR TKI distribution was erlotinib 50%, afatinib 31% and gefitinib 19%, whereas in the REFLECT primary study it was afatinib 45%, erlotinib 27% and gefitinib 27% (16), This result is in line with the reimbursement policy during 2015-2018, with erlotinib being the only EGFR TKI reimbursed until 2017, whereas the other two molecules were reimbursed afterwards (gefitinib the latest).
In the Romanian cohort, two-thirds (69%) of patients progressing on 1L EGFR TKI therapy underwent testing for the T790M resistance mutation, relatively similar to the rate of 71% reported in the primary REFLECT study (16). These figures are somehow lower compared with the testing rates of T790M of 70 – 90% communicated in other real-world European studies with a relatively similar design (21-25). The literature reports that T790M mutation is found at progression on 1G/2G EGFR TKIs in 50-60% of cases (3,10). Evaluating the results of our cohort, one may conclude that a higher number of patients would have had a positive result if all patients would have been tested (estimated 36-43 patients vs actual 28), and consequently, a chance for receiving osimertinib in 2L. The REFLECT study did not collect the reasons for not performing the T790M testing, but a German study (23) reported fast deterioration of clinical status, severe comorbid conditions, and patient’s decision as main causes for lack of T790M testing in progressive patients, which seem more related to the challenging tumor biopsy at progression. Guidelines recommend T790M testing upon the progression on EGFR TKI (3,8,12,26), and liquid biopsy is considered an acceptable method (12).
The suboptimal rate of T790M testing is one possible cause of the attrition rate observed in our cohort, where 31% of patients did not receive 2L treatment (among these, 9% deceased on 1L). A recent review showed that the attrition rate between 1L EGFR TKIs and 2L in EGFRm NSCLC is 36% in clinical trials, whereas in real-world studies it varies from 10% to 62% (27). Although in some cases an additional line of treatment may not translate in a clinical benefit, it is important to explore and address the local reasons of the attrition rates, and support the use the most efficacious therapy in 1L. Based on improved overall and CNS-specific efficacy and favourable toxicity profile demonstrated in the randomized clinical study FLAURA (11), osimertinib is now the preferred option for the 1L treatment of advanced EGFRm NSCLC (3,12,26). The first real-world studies also showed improved results with osimertinib in 1L. For example, in a retrospective analysis (28) including 172 patients with EGFRm NSCLC, the 12- and 18 month PFS was greater for osimertinib versus 1G/2G EGFR TKIs (80% and 70% vs. 64% and 39%, respectively, p<0.0036). The first prospective study exploring 1L osimertinib in 126 patients with advanced EGFRm NSCLC in real-life setting (29) showed median PFS of 18.9 months, median time to discontinuation 25.3 months and median OS not reached. While the long-term results of these real-world 1L osimertinib studies are awaited, the preliminary findings show better outcomes versus our cohort, where the 12- and 18-month PFS rates on 1L 1G/2G EGFR TKI were 50% and 21%, respectively, with a PFS of 12.0 months. t the time of this writing, reflex testing of EGFR mutations at diagnosis in Romania has significantly improved and is now aligned to updated guidelines, (3,12) and osimertinib is now reimbursed as 1L treatment.
The observational, retrospective nature of the REFLECT study, with a reduced number of inclusion and exclusion criteria is both a strength and a weakness: it provides an accurate snapshot of treatment and testing patterns at a specific timepoint, but it impedes the interpretation of results due to missing data and multiple confounding factors. In our analysis, a disadvantage was also the small sample size (n=90). A particular factor limiting the enrolment in Romania was the high number of patients with EGFRm NSCLC treated upfront with chemotherapy between 2015 and 2017, due to a delay of 1-3 months in the access to EGFR TKIs following the time lag in the Health Insurance Commission authorization. Nowadays, this drawback is solved, and the treatment authorization has become a rapid process, with access to targeted molecules provided as soon as the presence of the EGFR mutation is documented. However, the EGFR / T790M molecular testing is still not reimbursed.
5. Conclusions
This analysis is the first in Romania to provide detailed insights about clinical outcomes, type of treatments and T790M testing rate in EGFRm NSCLC patients treated in 1L with a 1G/2G EGFR TKI, before the standard of care in front-line setting changed to osimertinib. Survival outcomes in our cohort mirrored the data from randomized trials and other realworld studies. However, the T790M testing rate was suboptimal, with only 2 in 3 patients progressing on 1L EGFR TKI being tested for the resistance mutation. In addition, after 1L treatment, 1 in 3 patients did not receive any subsequent line. These findings emphasize the need for reflex testing at progression on 1L to ensure improved treatment strategies. In light of the current treatment landscape, our results stress the importance of upfront reflex testing to allow optimal outcomes through the selection of the most effective 1L treatments.
Abbreviations:
1G/2G – first- and second-generation
1L – first-line
2L – second-line
3L – third-line
CI – confidence interval
CNS – central nervous system
ECOG – Eastern Cooperative Oncology Group
EGFR – epidermal growth factor receptor
EGFR-m – EGFR-mutated
LMD – leptomeningeal disease
NSCLC – non-small cell lung cancer
OS – overall survival
rwPFS – real-world progression free survival
PFS – progression free survival
TKI(s) – tyrosine kinase inhibitor(s)
SD – standard deviation.
Statements:
Authors contributions: MD, AA, CLC, PC, PI, BG, MM, AN, MPF, AU, TEC have been involved in the acquisition and interpretation of data, critical revision of the article and approved the final version to be submitted. RL has been involved in the interpretation of data, critical revision of the article, supervision and approved the final version to be submitted. GT has been involved in the interpretation of data, critical revision of the article, and approved the final version to be submitted.
Consent for publication: As the corresponding author, I confirm that the manuscript has been read and approved for submission by all named authors.
Funding source: The REFLECT study was funded by AstraZeneca.
Statement of Ethics: Study approvals and waiver of informed consent form were obtained from all national and/or local Ethics Committees in participating countries. In Romania, the National Bioethics Committee for Medicines and Medical Device (Comisia Nationala de Bioetica a Medicamentului si a Dispozitivelor Medicale) has approved the study with a waiver of informed consent (approval number 3SNI/2019). Written consent from patients alive at data collection was not required.
Acknowledgements: Medical writing support was provided by Ana Maria Iordan (MD, MSc) of MedInteractiv (Bucharest, Romania) and funded by AstraZeneca in accordance with Good Publication Practice (GPP3) guidelines. Statistical analyses were provided by Planimeter Inc (Budapest, Hungary) and were funded by AstraZeneca.
Conflict of interests: MD declares honoraria for consultancy and speaking fee from Astellas, AstraZeneca, Aventis, Amgen, BMS, Eli Lilly, Janssen, MSD, Novartis, Pfizer, Roche, Sandoz, Servier; AA declares honoraria for consultancy and speaking fee from Amgen, AstraZeneca, BMS, MSD, Sandoz; CLC declares honoraria for advisory board consultancy from Boehringer Ingelheim, Merck, Novartis, Pfizer; lecture fees from AstraZeneca, Astellas, Bayer, BMS, Ipsen; travel grants from Alvogen, Boehringer Ingelheim, Merck; and educational grants from AstraZeneca; PC declares speaking fees from Accord, Amgen, Angelini Pharma, Astellas, AstraZeneca, Bayer, BMS, Egis, Eli Lilly, Ipsen, Johnson & Johnson, Merck, MSD, Novartis, Roche, Sandoz; honoraria from consultancy / advisory boards from Accord, Novartis, Roche, Sandoz, Zentiva; grants for travel & accommodation from A&D Pharma, Accord, Amgen, AstraZeneca, Bayer, BMS, Egis, Ipsen, Johnson & Johnson, Magnapharm, Merck, Pfizer, Roche, Novartis, Servier; and research funding/clinical trials investigator fees from from Amgen, Biocad, Celltrion, Genentech-Roche; PI declares honoraria for consultancy and speaking fee from Amgen, AstraZeneca, BMS, Boehringer Ingelheim, Merck Sharp&Dhome, Novartis, Pfizer, Roche Romania, Servier; BG declares honoraria/expenses from Accord, Amgen, Astellas, AstraZeneca, Bayer, BMS, Johnson&Johnson, Eli Lilly, Merck, MSD, Novartis, Pfizer; and consulting/advisory board from Astellas, Johnson&Johnson, Merck, Pfizer; and other (non-financial) from AstraZeneca; MM declares honoraria for consultancy from Egis, Ipsen, Novartis; advisory board consultancy from Angelini, Astellas, AstraZeneca, Bristol Myers Squibb, Egis, Ipsen, Johnson & Johnson/Janssen, Merck Serono, Merck Sharp & Dohme, Novartis, Pfizer, Roche, Servier; speaking fees from Accord, Amgen, Angelini, Astellas, AstraZeneca, Boehringer-Ingelheim, Bristol Myers Squibb, Egis, Roche, Ipsen, Johnson & Johnson/Janssen, Eli Lilly, Merck Serono, Merck Sharp & Dohme, Novartis, Pfizer, Sandoz, Solacium, Sanofi; and research funding/clinical trials investigator fees from Astellas, AstraZeneca, Bristol Myers Squibb, Daiichi-Sankyo, Exelixis, Glaxo SmithKline, Johnson & Johnson, Merck Serono, Merck Sharp & Dohme, Merkle, Novartis, Regeneron, Roche, USV Ltd; AN declares honoraria for consultancy and speaking fee from Acord, Astellas, AstraZeneca, BMS, Eli Lilly, Ipsen, Janssen, MSD, Novartis, Pfizer, Roche Sandoz; MPF declares speaking fees from Accord, AstraZeneca, BMS, Ipsen, Eli Lilly, MSD, Merck, Novartis, Pfizer, Roche, Sandoz; and research funding/clinical trials investigator fees from AbbVie, Amgen, AstraZeneca, GSK, MSD, Merck, Roche; AU declares honoraria from AstraZeneca, Bristol-Myers Squibb, Eli Lilly, Novartis, Sandoz, Teva; consulting or Advisory Role for Amgen, Bristol-Myers Squibb, Teva; and travel and accommodation expenses from Astellas Pharma and Teva; TEC declares honoraria for advisory /consultancy from AD Pharma, Amgen, Astellas, AstraZeneca, Boehringer Ingelheim, Bristol-Myers Squibb, Eli Lilly, Janssen, Merck Serono, Merck Sharp & Dohme, Novartis, Pfizer, Roche, Sanofi, Servier. RL and GT are employees of AstraZeneca Pharma Romania and have been involved in the review of the manuscript and in the decision to publish the results.
References:
- The Global Cancer Observatory, 2020, Romania, available at https://gco.iarc.fr/today/data/factsheets/populations/ 642-romania-fact-sheets.pdf, accessed on December 01, 2021.
- Inamura K. Lung Cancer: Understanding Its Molecular Pathology and the 2015 WHO Classification. Front Oncol. 2017;7:193. doi: 10.3389/fonc.2017.00193.
- Planchard D, Popat S, Kerr K, et al. Metastatic non-small cell lung cancer: ESMO Clinical Practice Guidelines for diagnosis, treatment and follow-up. Ann Oncol. 2018;29(Suppl 4):iv192-iv237. doi: 10.1093/annonc/mdy275.
- Carcereny E, Morán T, Capdevila L, et al. The epidermal growth factor receptor (EGRF) in lung cancer. Transl Respir Med. 2015;3:1. doi: 10.1186/s40247-015-0013-z.
- Gelatti ACZ, Drilon A, Santini FC. Optimizing the sequencing of tyrosine kinase inhibitors (TKIs) in epidermal growth factor receptor (EGFR) mutation-positive non-small cell lung cancer (NSCLC). Lung Cancer. 2019;137:113-122. doi: 10.1016/j.lungcan.2019.09.017.
- Vansteenkiste J, Wauters E. Tyrosine kinase inhibition of EGFR: a successful history of targeted therapy for NSCLC since 20 years. Ann Oncol. 2018;29(suppl_1):i1-i2. doi: 10.1093/annonc/mdx724.
- Reck M, Popat S, Reinmuth N, De Ruysscher D, Kerr KM, Peters S; ESMO Guidelines Working Group. Metastatic non-small-cell lung cancer (NSCLC): ESMO Clinical Practice Guidelines for diagnosis, treatment and follow-up. Ann Oncol. 2014;25 Suppl 3:iii27-39. doi: 10.1093/annonc/mdu199.
- Novello S, Barlesi F, Califano R, Cufer T, Ekman S, Levra MG, Kerr K, Popat S, Reck M, Senan S, Simo GV, Vansteenkiste J, Peters S; ESMO Guidelines Committee. Metastatic non-small-cell lung cancer: ESMO Clinical Practice Guidelines for diagnosis, treatment and follow-up. Ann Oncol. 2016;27(suppl 5):v1-v27. doi: 10.1093/annonc/mdw326.
- Westover D, Zugazagoitia J, Cho BC, Lovly CM, Paz-Ares L. Mechanisms of acquired resistance to first- and secondgeneration EGFR tyrosine kinase inhibitors. Ann Oncol. 2018;29(suppl_1):i10-i19. doi: 10.1093/annonc/mdx703.
- Santoni-Rugiu E, Melchior LC, Urbanska EM, et al. Intrinsic resistance to EGFR-Tyrosine Kinase Inhibitors in EGFR-Mutant Non-Small Cell Lung Cancer: Differences and Similarities with Acquired Resistance. Cancers (Basel). 2019;11(7):923. doi: 10.3390/cancers11070923.
- Ramalingam SS, Vansteenkiste J, Planchard D, et al. Overall Survival with Osimertinib in Untreated, EGFR-Mutated Advanced NSCLC. N Engl J Med. 2020;382(1):41-50. doi: 10.1056/NEJMoa1913662.
- Planchard D, Popat S, Kerr K, et al. Metastatic non-small cell lung cancer: ESMO Clinical Practice Guidelines for diagnosis, treatment and follow-up. Originally published in Ann Oncol. 2018;29(Suppl 4):iv192-iv237. Updated version published 15 September 2020 by the ESMO Guidelines Committee, available at https://www.esmo.org/guidelines/lungand-chest-tumours/clinical-practice-living-guidelines-metastatic-non-small-cell-lung-cancer, accessed on December 01, 2021.
- Petracci F, Ghai C, Pangilinan A, Suarez LA, Uehara R, Ghosn M. Use of real-world evidence for oncology clinical decision making in emerging economies. Future Oncol. 2021;17(22):2951-2960. doi: 10.2217/fon-2021-0425.
- Di Maio M, Perrone F, Conte P. Real-World Evidence in Oncology: Opportunities and Limitations. Oncologist. 2020;25(5):e746-e752. doi: 10.1634/theoncologist.2019-0647.
- Nazha B, Yang JC, Owonikoko TK. Benefits and limitations of real-world evidence: lessons from EGFR mutationpositive non-small-cell lung cancer. Future Oncol. 2021;17(8):965-977. doi: 10.2217/fon-2020-0951.
- Addeo A, Hochmair M, Janzic U, et al. Treatment patterns, testing practices, and outcomes in the pre-FLAURA era for patients with EGFR mutation-positive advanced NSCLC: a retrospective chart review (REFLECT). Ther Adv in Med Oncol. 2021. doi: 10.1177/17588359211059874.
- Hsu WH, Yang JC, Mok TS, Loong HH. Overview of current systemic management of EGFR-mutant NSCLC. Ann Oncol. 2018;29(suppl_1):i3-i9. doi: 10.1093/annonc/mdx702.
- Takeda M, Nakagawa K. First- and Second-Generation EGFR-TKIs Are All Replaced to Osimertinib in Chemo-Naive EGFR Mutation-Positive Non-Small Cell Lung Cancer? Int J Mol Sci. 2019;20(1):146. doi: 10.3390/ijms20010146.
- Vrdoljak E, Bodoky G, Jassem J, et al. Cancer Control in Central and Eastern Europe: Current Situation and Recommendations for Improvement. Oncologist. 2016;21(10):1183-1190. doi: 10.1634/theoncologist.2016-0137.
- Cufer T, Ciuleanu TE, Berzinec P, et al. Access to Novel Drugs for Non-Small Cell Lung Cancer in Central and Southeastern Europe: A Central European Cooperative Oncology Group Analysis. Oncologist. 2020;25(3):e598-e601. doi: 10.1634/theoncologist.2019-0523.
- Cuppens K, Lodewyckx L, Demedts I, et al. Real-World Treatment Patterns, Epidermal Growth Factor Receptor (EGFR) Testing and Outcomes in EGFR-Mutated Advanced Non-small Cell Lung Cancer Patients in Belgium: Results from the REVEAL Study. Drugs Real World Outcomes. 2021;8(2):141-152. doi: 10.1007/s40801-021-00243-w.
- Shah R, Girard N, Nagar SP, et al. European and US Real-World Treatment Patterns in Patients with Epidermal Growth Factor Receptor Mutation-Positive Non-Small Cell Lung Cancer: A Retrospective Medical Record Review. Drugs Real World Outcomes. 2021;8(4):537-545. doi: 10.1007/s40801-021-00261-8.
- Magios N, Bozorgmehr F, Volckmar AL, et al. Real-world implementation of sequential targeted therapies for EGFRmutated lung cancer. Ther Adv Med Oncol. 2021;13:1758835921996509. doi: 10.1177/1758835921996509.
- Pereira I, Gaspar C, Pina M, Azevedo I, Rodrigues A. Real-World T790M Mutation Frequency and Impact of Rebiopsy in Patients With EGFR-Mutated Advanced Non-Small Cell Lung Cancer. Cureus. 2020;12(12):e12128. doi: 10.7759/cureus.12128.
- Reale ML, Chiari R, Tiseo M, et al. Be-TeaM: An Italian real-world observational study on second-line therapy for EGFR-mutated NSCLC patients. Lung Cancer. 2020;140:71-79. doi: 10.1016/j.lungcan.2019.12.006.
- Hanna NH, Schneider BJ, Temin S, et al. Therapy for Stage IV Non-Small-Cell Lung Cancer Without Driver Alterations: ASCO and OH (CCO) Joint Guideline Update. J Clin Oncol. 2020;38(14):1608-1632. doi: 10.1200/JCO.19.03022.
- Roeper J, Kurz S, Grohé C, Griesinger F. Optimizing therapy sequence to prevent patient attrition in EGFR mutationpositive advanced or metastatic NSCLC. Future Oncol. 2021;17(4):471-486. doi: 10.2217/fon-2020-0854.
- Lee CS, Ahmed I, Miao E, et al. A real world analysis of first line treatment of advanced EGFR mutated non-small cell lung cancer: A multi-center, retrospective study. J Oncol Pharm Pract. 2021:10781552211020798. doi: 10.1177/10781552211020798.
- Lorenzi M, Ferro A, Cecere F, et al. First-Line Osimertinib in Patients with EGFR-Mutant Advanced Non-Small Cell Lung Cancer: Outcome and Safety in the Real World: FLOWER Study. Oncologist. 2021. doi: 10.1002/onco.13951.

*The count excludes deceased patients in each line. Due to rounding, percentages may not always be 100%.
Note: The patient discontinuing 1L from unknown reasons started a new therapy line without documented progression, which is considered a per-protocol event.
