


Author(s) :
Tiberiu Popescu1, Angelica Chiorean2, 3, Noemi Schultes4, Catalin Iacob1, Dan Eniu5, 6
1 Department of Radiation Oncology, RTC Amethyst, Cluj, Romania
2 Department of Imaging and Radiology, Iuliu Hatieganu University of Medicine and Pharmacy, Cluj, Romania
3 MedImages Clinic, Cluj, Romania
4 Department of Medical Physics, RTC Amethyst, Cluj, Romania
5 Department of Surgical Oncology, Iuliu Hatieganu University of Medicine and Pharmacy, Cluj, Romania
6 Department of Surgical Oncology, Prof. Dr. Ion Chiricuta Institute of Oncology, Cluj, Romania
Corresponding author: Tiberiu Popescu, Email: tiberiu.popescu@amethyst-radiotherapy.com
Publication History: Received - , Revised - , Accepted - , Published Online - December 2021.
Copyright: © The author(s). Published by Casa Cărții de Știință.
User License: Creative Commons Attribution – NonCommercial (CC BY-NC)

 PDF
 Share
Highlights
Abstract
Stereotactic body radiation therapy (SBRT) is a type of radiotherapy which uses a high radiation dose delivered in a single or a few fractions and is employed with local curative intent for early-stage cancer, relapsed cancer or in the oligometastatic setting. The aim of this case report is to illustrate the potential of this technique in the salvage re-irradiation of a late isolated in field regional relapse after bilateral breast cancer.
This is the case of a 65-years-old woman with a metachronous bilateral breast cancer (left side-1998, stage IIB, Luminal type; right side-2010, stage IIA, Her2 positive) who received both chemo- and endocrine systemic therapy, underwent surgery and was irradiated on both sides, with a late solitary recurrence in her left internal mammary node chain (2018) treated by SBRT re-irradiation (40 Gy in 5 fractions). Three years after salvage SBRT, under Palbociclib+Letrozole and thorough follow-up protocol, she is still in clinical complete remission, with a normal CA 15-3 and metabolically inactive residual mass on PET-CT, negative on a recent biopsy.
SBRT is becoming a hallmark of oligometastatic disease management and can be invaluable in patients subjected to prior radiotherapy.
1. Introduction:
Stereotactic body radiation therapy (SBRT) is a hypo-fractionated intensity modulated, highly conformal type of external beam radiotherapy which, combines concepts of tight margins, high dose fall-off, motion control and image-guided delivery. As the tumor receives a very high dose per fraction in a limited number of sessions, it has become a preferred approach for the treatment of primary early-stage cancer, especially in the elderly (1,2), oligometastatic disease (3,4) or relapse, as a salvage solution inside or outside a previously irradiated area (5).
2. Case report:
2.1 Clinical history:
This is the case study of a long-term cancer survivor, now a 68-year woman, with a positive family history of hereditary malignancy (grandparents – gastric and genital cancers), diagnosed with a metachronous bilateral breast cancer and with a recent oligo-recurrence in the left internal mammary nodes chain. She survived stage II B, Luminal type, G2 left breast invasive ductal carcinoma in 1998, for which, she received 6 cycles of Epirubicin – Cyclophosphamide, a left modified radical mastectomy (MRM) and adjuvant 2D radiotherapy (RT) and endocrine therapy (Tamoxifen for only 2 years due to poor tolerance).
Contralateral breast cancer of a different biology was diagnosed 12 years later, as a G3 Her2-positive invasive ductal carcinoma. She underwent upfront surgery (right MRM) in 2010, pT2N0M0L0Pn1, stage IIA, followed by 6 cycles of adjuvant Paclitaxel, 3D conformal RT and Trastuzumab for one year, but no adjuvant endocrine therapy, which, was declined. The patient remained free of disease at the following regular visits.
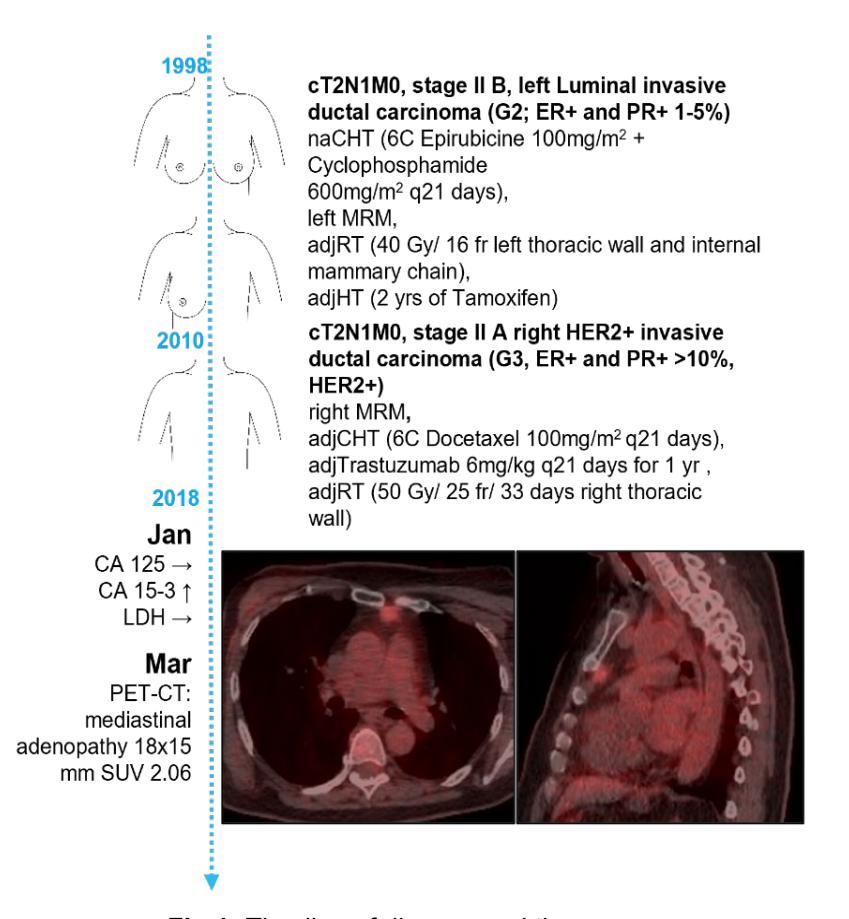
Fig.1: Timeline of disease and therapy
Eight years later, in January 2018, a sudden rise in CA 15-3 level (=51.34 U/mL) prompted a new PET-CT, which, described an upper left internal mammary node (IMN) of 18×15 mm, metabolically highly suspicious of metastasis (timeline in Fig. 1).
A couple of weeks later, a contrastenhanced, thoracic CT scan showed a growing left parasternal mass in the 2nd left intercostal space measuring 21 mm. An ultrasound-guided biopsy was recommended for the assessment of tumor biology, but it was declined by the patient, as well as any invasive resection procedure, due to potential risks related to the proximity of major blood vessels.
2.2 Treatment description:
This left IMN was considered a solitary late recurrence (oligo-recurrence) (6), 20 years after her initial left-sided cancer. The 1998 RT full dosimetry could not be retrieved, the only available information being that she received 40 Gy/16 frwith 2 thoracic tangential fields plus an anterior axillary and supraclavicular field, all delivered by a Theratronics 100 Cobalt machine. Considering the skin late visible toxicity (telangiectasia) and the in-house protocol at that time in the institution where she received RT, we estimated that the left IMN received between 20 and 40% of the prescribed dose. SBRT was proposed in the Multidisciplinary Tumor Board. A 4D-CT simulation was performed in supine position, with acquisition of 3-mm slice sections. The target volume was defined as gross tumor volume (GTV) and its different positions relative to breathing phases (0%, 25%, 75%, 100%) were integrated into an internal target volume (ITV). A 5 mm ITV to planning target volume (PTV) margin was generated. Forty Gy were prescribed to the PTV 80% isodose and delivered every-other-day in 5 fractions by intensity-modulated radiation therapy (IMRT) step and shoot, 6 MV, by an Elekta Infinity linear accelerator (LINAC) with an
Agility 5 mm multileaf collimator (MLC). Image-guided radiation therapy (IGRT) with cone beam CT was used for every treatment session. The heart, large vessels, left and right lungs, spinal cord, spinal canal, chest wall and skin were defined as organs at risk and were kept within dosimetry constraints. Excellent coverage of the target volume was obtained (ITV V40=100%, PTV V40= 90.22%), while the heart, left and right lungs were optimally spared, with a mean dose of 2.8, 2.4 and 2.1 Gy, respectively. The spinal cord received a negligible dose. The great vessels and chest wall were kept within constraints (Fig. 2). After completion of SBRT, the patient accepted and started a CDK4/6 inhibitor (Palbociclib 125 mg po qdfor days 1-21/28) and endocrine therapy with Letrozole 2.5 mg po qd.
2.3 Follow up and Results:
No acute toxicity whatsoever was recorded during SBRT or in next 3 months (G0 Common Terminology Criteria for Adverse Events – CTCAE 4.0) – the patient was clinically asymptomatic and without any changes at the irradiation site. She was followed at every three months with clinical exam, contrast enhanced CT and CA 15-3 for two and a half years. CTs showed a regressive scar lesion, with no symptoms or signs of radiation fibrosis in the vicinity. Yearly PET-CT showed no pathological uptake. In February 2021 the clinical examination identified a left parasternal mass that elicited a biopsy, which, proved negative for malignancy. As of her last PET-CT in August 2021, the patient has been free from disease and continues the treatment with Palbociclib and Letrozole.
3. Discussion:
This case is particular for several reasons. Firstly, because of the timing and topography of an isolated oligo-recurrence after a bilateral metachronous cancer, in a
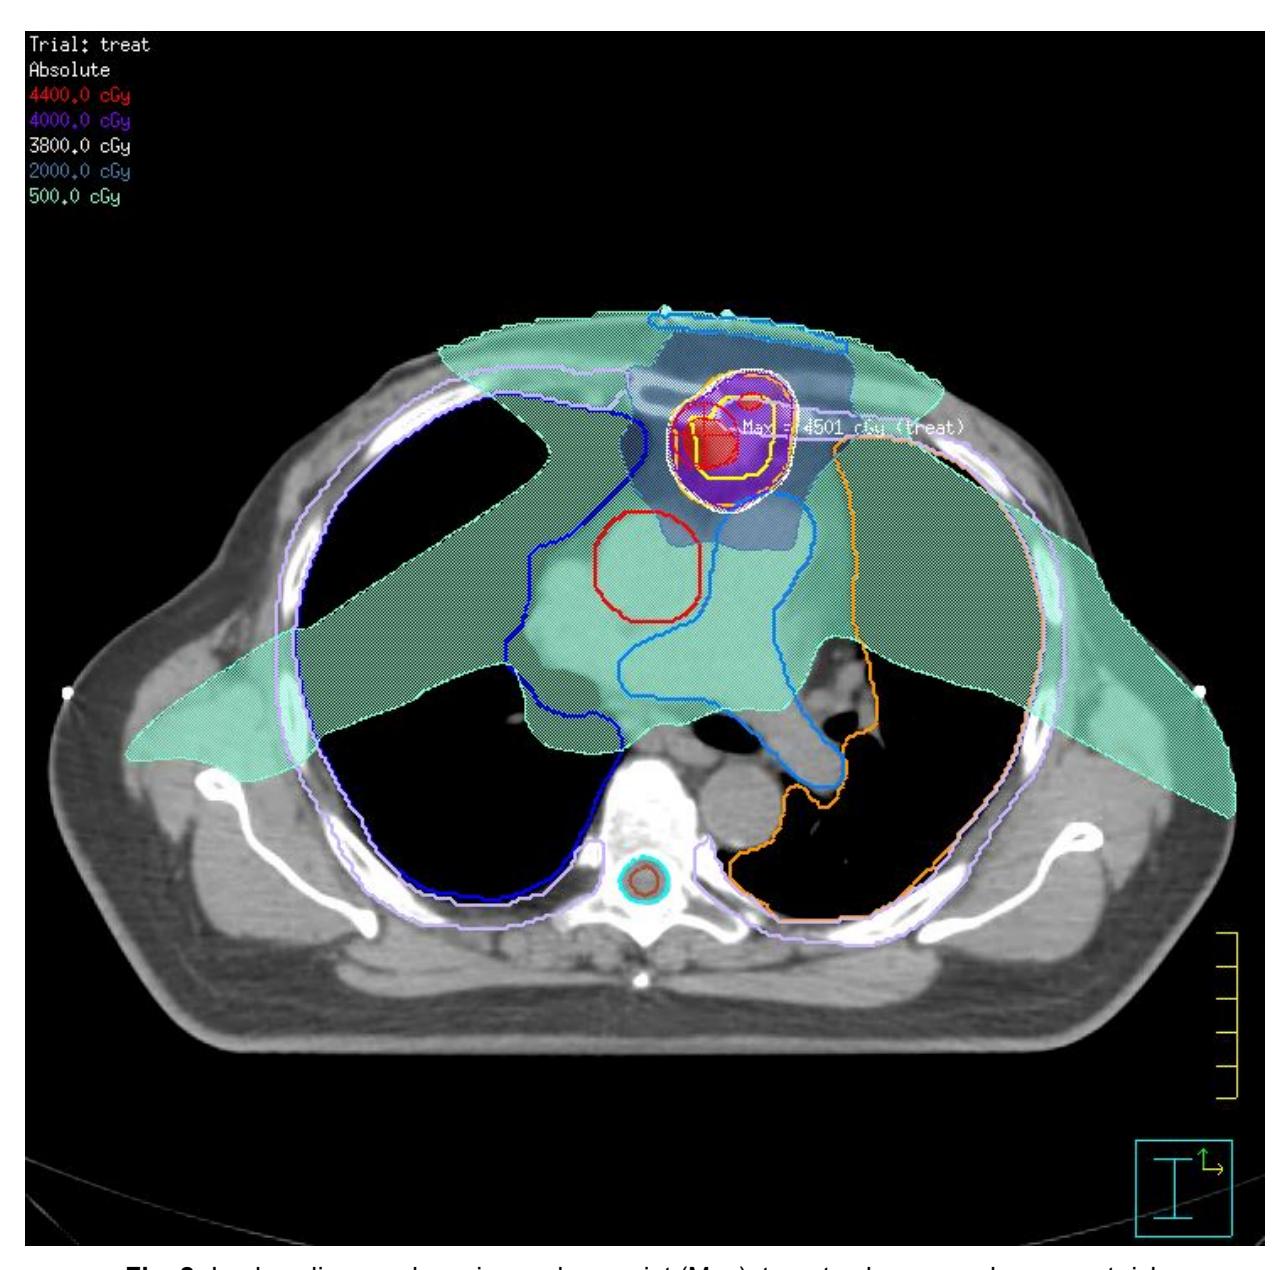
Fig. 2: Isodose lines and maximum dose point (Max), target volumes, and organs at risk
previously irradiated area. Secondly, because of the delicate situation with lack of accurate previous dosimetry available, and finally, from the dire perspective of virtually no available local ablative options (surgery, radio-frequency ablation, or cryotherapy were not suitable due to the endothoracic position and the proximity of major vessels). Since the precise biology of this recurrence was not known, a left breast cancer origin was more probable, although the Her2+ biology did not exclude a contralateral origin as a ‘true’ metastasis.
In the light of the new consensus on the characterization and classification of oligometastatic disease by Guckenberger et al., this patient can be described as having genuine, de-novo, metachronous oligo-recurrence (6). Since there were no other metastases, a less aggressive biology of the tumor was warranted, which, made the patient an ideal candidate for aggressive local radical treatment.
Recurrence in the IMN is rare at 1.5% but the intrathoracic topography of IMN limits conventional ablative approaches such as surgery, at least among gynecology and breast surgical oncologists. The literature regarding IMN excision is rather scarce (7). On the other hand, SBRT seems to be a matched pair for oligometastatic disease in modern Oncology. Available studies tend to gather oligometastases of different primary origins and to different sites. SABR-COMET trial, the icon of ablative treatment in oligometastatic disease, showed a 5-year OS rate of 42.3% in the experimental ablative treatment arm versus 17.7% in the standard of care arm (4). Twenty percent of the ablative treatment arm were patients with breast cancer. In Lehrer’s et al. metaanalysis on the safety and survival associated with ablative stereotactic radiotherapy for patients with oligometastatic cancers, 13.1% of these were breast cancer patients [8]. Safety can be of real concern in such re-irradiation settings as the above (potential serious skin, lung, chest wall and heart toxicity because of prior irradiation), where dosimetry and patient chart from previous irradiation were difficult to retrieve.
Table 1. Summary of studies employing SBRT for the treatment of oligometastatic disease in breast cancer which, include metastasis to the IMNs
| Study | Patients (lesions no) | Type | Site of metastases (no of lesions) | Therapy (dose) | Outcome | Toxicity |
|---|---|---|---|---|---|---|
| Trovo M, et al., 2017 [9] | 54 (92) | Prospective phase II multicentric trial | Bone (60), Lymph nodes (23), Lung (4), Liver (5) | SBRT*/IMRT (35-40Gy in 3 fr/60 Gy in 25 fr) | 1-y PFS 75%, 2-y PFS 53%, 2-y LC 97%, 2-y OS 95% | no ≥ G3, 2 pts G2 (pain and fatigue) |
| Milano MT, et al., 2012[12] | 39 (47) | Prospective | Lung (11), Thoracic lymph nodes (9), Liver (13), Pelvis/abdomen (2), Brain (1), Bone (11) | SBRT (mostly 50Gy in 5 fr) | 2-y OS 74%, 2-y FFDM 52%, 2-y LC 87%, 6-y OS 47%, 6-y FFDM 36%, 6-y LC 87% | no ≥ G4-5, 1 pts G3 (non malignant pleural and pericardial effusion) |
| Milano MT, et al., 2009[13] | 40 (85) | Prospective pilot | Liver (33), Lung (19), Bone (17), Thoracic lymph nodes (14), Pelvic/abdominal lymph nodes (2) | SBRT (N/A) | 4-y OS 59%, 4-y PFS 38%, 4-y LC 89% | N/A |
*Preferred treatment, PFS – progression free survival, OS – overall survival
The addition of radical radiation therapy for breast oligometastases on top of the systemic treatment almost doubled the currently described 2-years PFS of 30% (PFS 53%), with 2-years local control (LC) and overall survival (OS) > 90% [9]. There are extremely few studies of SBRT exclusively for breast cancer, and even less dealing specifically with lymph nodes oligo- recurrence (Table 1) [10]. The phase IIR/III trial NRG BR002 (NCT02364557) was designed to compare standard of care therapy ± SBRT and/or surgical ablation for newly oligometastatic breast cancer. As a side note, by including a Translational Research approach in its design, it could ingeniously set the stage for the future [11].
Lastly, this case also emphasizes the problem of adherence to endocrine treatment. This is generally grim, with up to 1/4 patients enrolled in clinical trials and 3/4 patients in community practice settings who prematurely discontinue adjuvant endocrine therapy, mainly because of poor management of side effects [14]. This greatly diminishes the advantages offered in terms of reduced risk of locoregional and distant failure, or death from breast cancer [15].
4. Conclusion:
Radiation Oncology underwent dramatic technological and conceptual development, with SBRT as a safe and effective approach of re-irradiation. This case tells the story of radiotherapy in brief, from Cobalt machines, conformal radiotherapy to one of the most sophisticated means of radiation delivery, namely SBRT, as an efficient, safe, and curative in intent option for isolated recurrences, even in previously irradiated areas.
Abbreviations:
SBRT – Stereotactic Body Radiation Therapy
PET-CT – Positron Emission Tomography – Computed Tomography
CA-15-3 – Cancer Antigen 15-3
MRM – modified radical mastectomy
RT – radiotherapy
IMN – internal mammary nodes
GTV – gross tumor volume
ITV – internal target volume
PTV – planning target volume
IMRT – intensity-modulated radiation therapy
LINAC – linear accelerator
MLC – multileaf collimator
IGRT – image-guided radiation therapy
CBCT – cone beam CT
CTCAE – Common Terminology Criteria for Adverse Events
PFS – progression free survival
OS – overall survival
Statements:
Author’s contributions:TP wrote the paper, NS provided the technical details, CI detailed the history of the patient, AC and DE reviewed the paper, TP reviewed and approved the final version.
Consent for publication: As the corresponding author, I confirm that the manuscript has been read and approved for submission by all co-authors.
Conflicts of interest: All authors declare having no competing interests associated with this publication.
Funding resources: This research did not receive any specific grant from funding agencies in the public, commercial, or not-for-profit sector.
Informed Consent: The informed consent was obtained from the patient(s) for publication and any accompanying images.
Statement of Ethics: The accompanying manuscript does not contain any studies carried out by the authors on humans or animals.
Ethical Approval: The treatment strategy/study protocol was approved by a local tumor board/ethics committee.
References:
- Shinde A, Li R, Kim J, et al. Stereotactic body radiation therapy (SBRT) for early-stage lung cancer in the elderly. Semin Oncol. 2018 Aug;45(4):210-219.
- Chang JY, Mehran RJ, Feng L, et al. Stereotactic ablative radiotherapy for operable stage I non-small-cell lung cancer (revised STARS): long-term results of a single-arm, prospective trial with prespecified comparison to surgery. Lancet Oncol. 2021 Oct;22(10):1448-1457.
- Alongi F, Arcangeli S, Filippi AR, et al. Review and uses of stereotactic body radiation therapy for oligometastases. Oncologist. 2012;17(8):1100-7.
- Palma DA, Olson R, Harrow S, et al. Stereotactic Ablative Radiotherapy for the Comprehensive Treatment of Oligometastatic Cancers: Long-Term Results of the SABR-COMET Phase II Randomized Trial. J Clin Oncol. 2020 Sep 1;38(25):2830-2838.
- Miyata M, Ohguri T, Yahara K, et al. Salvage radiotherapy for second oligo-recurrence in patients with breast cancer. J Radiat Res. 2018 Jan 1;59(1):58-66. doi: 10.1093/jrr/rrx066. PMID: 29182763; PMCID: PMC5778500.
- Guckenberger M, Lievens Y, Bouma AB, et al. Characterisation and classification of oligometastatic disease: a European Society for Radiotherapy and Oncology and European Organisation for Research and Treatment of Cancer consensus recommendation. Lancet Oncol. 2020 Jan;21(1):e18-e28.
- Qingqing H, Jian Z, Dayong Z, et al. Robot-Assisted Internal Mammary Lymph Node Chain Dissection for Breast Cancer Clin Breast Cancer. 2018;18(4):e441-e445.
- Lehrer EJ, Singh R, Wang M, et al. Safety and Survival Rates Associated With Ablative Stereotactic Radiotherapy for Patients With Oligometastatic Cancer: A Systematic Review and Meta-analysis. JAMA Oncol. 2021 Jan 1;7(1):92-106. doi: 10.1001/jamaoncol.2020.6146. PMID: 33237270; PMCID: PMC7689573.
- Trovo M, Furlan C, Polesel J, et al. Radical radiation therapy for oligometastatic breast cancer: Results of a prospective phase II trial. Radiother Oncol 2018;126(1):177-180.
- Matushita H, Jingu K, Umezawa R, et al. Stereotactic Radiotherapy for Oligometastases in Lymph Nodes— A Review. Technol Cancer Res Treat. 2018; 17: 1-8.
- Chmura SJ, Winter KA, Al-Hallaq AH, et al. NRG-BR002: A phase IIR/III trial of standard of care therapy with or without stereotactic body radiotherapy (SBRT) and/or surgical ablation for newly oligometastatic breast cancer (NCT02364557). Journal of Clinical Oncology 2019 37:15_suppl, TPS1117-TPS1117
- Milano MT, Katz AW, Zhang H, et al. Oligometastases treated with stereotactic body radiotherapy: long-term follow-up of prospective study. Int J Radiat Oncol Biol Phys. 2012;83(3):878-86.
- Milano MT, Zhang H, Metcalfe SK, et al. Oligometastatic breast cancer treated with curative-intent stereotactic body radiation therapy. Breast Cancer Res Treat. 2009;115(3):601-8.
- Brockway JP, Shapiro CL. Improving Adherence to Endocrine Therapy in Women With HR-Positive Breast Cancer. Oncology (Williston Park). 2018;32(5):235-7, 249.
- Early Breast Cancer Trialists’ Collaborative Group. Effects of chemotherapy and hormonal therapy for early breast cancer on recurrence and 15-year survival: an overview of the randomised trials. Lancet 2005; 365: 1687-717.

